


Two people can step on the same scale, see the same number, and carry substantially different metabolic risk. That sounds like a contradiction until you look beneath the skin.
The soft fat that can be pinched at the waist is subcutaneous. It sits between skin and muscle, and it is largely inert. Visceral fat sits deeper, inside the abdominal wall, packed around the liver, intestines and other organs. It is metabolically active tissue that releases fatty acids and inflammatory signalling molecules directly into the portal circulation feeding the liver. Gram for gram, it behaves very differently.
A bathroom scale cannot distinguish the two. Neither can a mirror, and neither, with any precision, can a tape measure. Yet the distinction drives a great deal of what happens to blood pressure, triglycerides, insulin sensitivity and liver fat over time.
This article is about that measurement problem: what visceral fat does, how laboratories and imaging departments actually quantify it, and what happens when a therapy is designed to target it specifically rather than to reduce body weight in general. The clearest worked example of that last point is tesamorelin, an approved prescription medicine with an unusually narrow indication and a label that goes out of its way to say it is not a weight-loss drug. If you are already following supply, you can check current tesamorelin availability before reading on.
Key takeaways
- Visceral fat is metabolically active and drains into the liver’s blood supply; subcutaneous fat largely is not.
- Body weight and BMI cannot distinguish the two, and waist circumference only approximates the difference.
- Cross-sectional imaging is the reference method; DXA and bioimpedance are convenient but estimate rather than measure.
- Tesamorelin is approved only for reducing excess abdominal fat in adults with HIV-associated lipodystrophy, and its label states it is weight neutral.
- In the registration trials the benefit depended on continuing treatment; participants switched to placebo regained visceral fat.
View the full product specifications →
Two People, the Same Weight, Very Different Risk
Body mass index was designed in the nineteenth century as a population statistic, not a clinical measure of an individual. It divides weight by the square of height and says nothing at all about what the weight is made of. A muscular athlete and a sedentary person of identical height and weight receive identical scores.
The same blindness applies within fat tissue itself. Two people with matching weight, matching BMI and even matching total body fat can differ considerably in where that fat sits. One may carry it predominantly under the skin across hips and thighs. The other may carry a smaller total amount, but concentrated inside the abdomen.
The second pattern tracks more closely with insulin resistance, elevated triglycerides, reduced HDL cholesterol, raised blood pressure and fat accumulation in the liver. This is why clinicians have long noticed that some people with apparently modest weight develop metabolic problems while others considerably heavier do not. The phenomenon has been described as metabolically healthy obesity at one end and normal-weight metabolic obesity at the other, and the underlying variable in both cases is distribution rather than quantity.
The practical consequence is that a scale reading, on its own, answers a question nobody particularly needs answered. It reports mass. The clinically interesting quantity is composition and location.
What Visceral Fat Does That Subcutaneous Fat Does Not
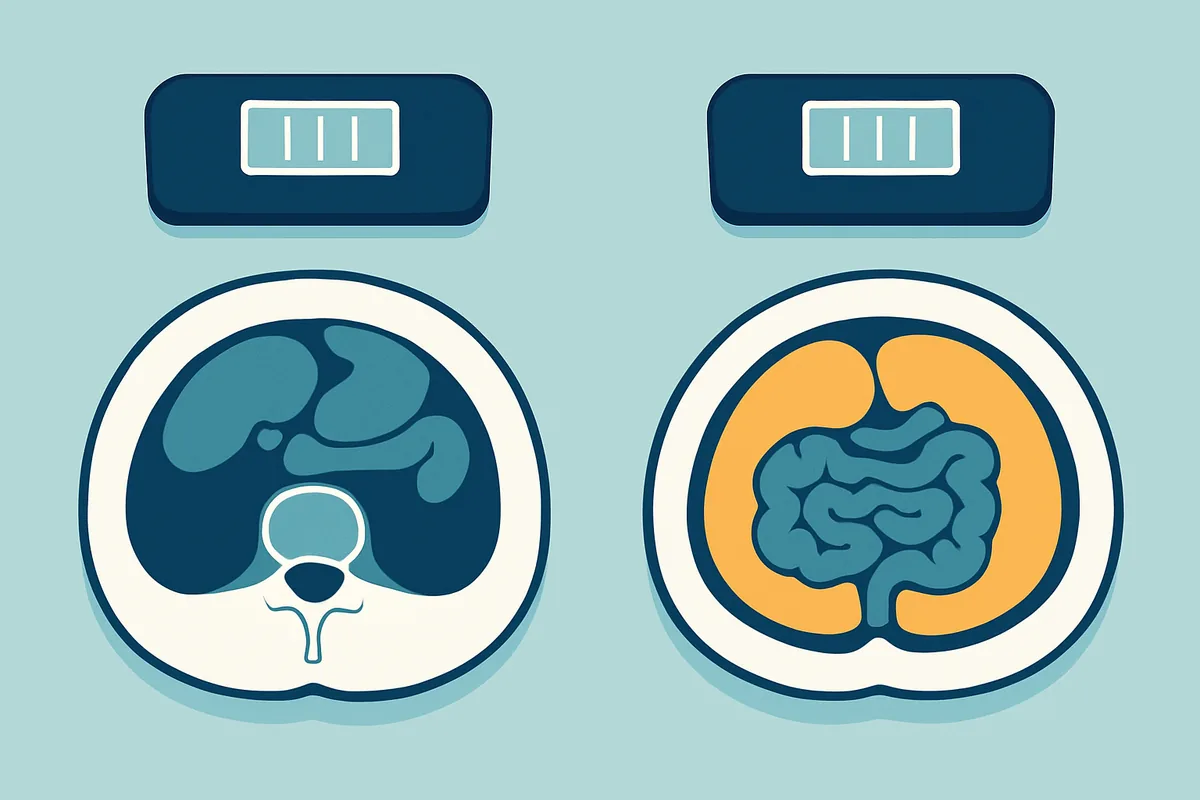
Fat tissue is not a passive fuel depot. It is an endocrine organ that secretes signalling molecules, and visceral fat is considerably more active in this respect than subcutaneous fat.
Two features explain most of the difference. The first is anatomical drainage. Visceral fat sits within the territory drained by the portal vein, which carries blood directly to the liver before it reaches general circulation. Free fatty acids and inflammatory mediators released from visceral fat therefore arrive at the liver first and at high concentration, where they influence glucose output, lipoprotein production and fat storage within liver cells themselves. Subcutaneous fat drains into systemic circulation, where its output is diluted before reaching any organ in quantity.
The second is cellular behaviour. Visceral adipocytes are more responsive to the hormonal signals that trigger fat release, less responsive to insulin’s instruction to hold onto stored fat, and more densely populated with immune cells that produce inflammatory cytokines. The tissue is simply busier, and more of what it produces reaches somewhere consequential.
This is why measurements of visceral fat correlate with metabolic markers more strongly than total body fat does, and why interventions that shift visceral fat specifically can improve those markers out of proportion to the weight change involved.
How Visceral Fat Is Actually Measured
Because the tissue is internal, measuring it properly requires seeing inside the abdomen. The methods available differ substantially in accuracy, cost and radiation exposure.
Computed tomography is the historical reference standard. A single cross-sectional slice, conventionally taken at the level of the fourth or fifth lumbar vertebra, is analysed by separating pixels according to their radiodensity. Fat occupies a distinct and narrow band of values, which allows the visceral compartment to be traced inside the abdominal wall and its area calculated in square centimetres. The method is precise and reproducible, which is exactly why it is used as the primary endpoint in trials. It also involves ionising radiation, which limits how often it can reasonably be repeated.
Magnetic resonance imaging achieves comparable accuracy without radiation, by exploiting the different behaviour of fat and water protons in a magnetic field. It is slower and considerably more expensive, and access is more limited.
Dual-energy X-ray absorptiometry, the same scan used for bone density, estimates visceral fat within the abdominal region using algorithms calibrated against CT. Radiation exposure is very low and cost is modest. The output is an estimate derived from a model rather than a direct measurement, and agreement with CT is good at a population level while being less reliable for any individual.
Bioelectrical impedance devices, including consumer body composition scales, pass a small current through the body and infer composition from the resistance encountered. They are strongly affected by hydration, recent meals, exercise and skin temperature. Their visceral fat readings are best understood as a rough index for tracking trends within one person on one device, not as a measurement comparable to imaging.
| Method | What it produces | Radiation | Practical role |
|---|---|---|---|
| CT, single slice | Direct visceral fat area in cm² | Yes | Reference standard, trial endpoints |
| MRI | Direct visceral fat volume | No | Research, where cost allows |
| DXA | Model-based estimate of visceral fat | Very low | Reasonable clinical compromise |
| Bioimpedance | Index derived from resistance | No | Trend tracking only, device-specific |
| Waist circumference | Proxy for combined abdominal fat | No | Cheap, useful, cannot separate compartments |
Waist circumference deserves its own note. It is free, requires no equipment beyond a tape, and predicts metabolic risk better than BMI. It also cannot distinguish visceral from subcutaneous fat, and technique matters more than most people realise: measurement site, whether the tape is taken at the end of a normal exhalation, and tape tension all shift the result by amounts comparable to months of genuine change.
Why HIV-Associated Lipodystrophy Is Its Own Problem
For some adults living with HIV, long-term antiretroviral therapy has been accompanied by changes in how the body distributes fat. The pattern can involve accumulation of visceral fat in the abdomen, sometimes alongside loss of subcutaneous fat from the face, arms and legs.
Several factors appear to contribute, including effects of particular older antiretroviral agents on fat cell function and mitochondria, the inflammatory effects of the infection itself, and metabolic recovery following treatment. Newer regimens have reduced but not eliminated the problem.
What makes this clinically distinct is that the abdominal accumulation can occur without a corresponding increase in overall body weight, and sometimes alongside subcutaneous fat loss elsewhere. Generic advice to lose weight is a poor fit for someone whose limbs are already losing fat tissue while their abdomen accumulates it. The problem is not quantity but distribution, and a scale is close to useless for tracking it.
This is the population in which tesamorelin was developed and for which it is approved.
Limited monthly batches
Tesamorelin 10mg
GHRH analogue · 99%+ HPLC purity · Research-grade peptide
What the Tesamorelin Trials Measured, and For How Long
Tesamorelin is a synthetic analogue of growth hormone-releasing hormone. Rather than supplying growth hormone directly, it stimulates the pituitary to produce more of the body’s own, which in turn raises insulin-like growth factor 1 and promotes the breakdown of fat. It is given as a daily subcutaneous injection into the abdomen.
Approval rested on two multicentre, randomised, double-blind, placebo-controlled trials enrolling 412 and 404 adults with HIV-associated lipodystrophy. Each ran for 26 weeks, followed by a 26-week extension, and the primary endpoint was the percentage change in visceral fat measured by CT.
At 26 weeks, the first trial reported a mean reduction in visceral fat of 18 percent on tesamorelin against a 2 percent increase on placebo. The second reported a 14 percent reduction against a 2 percent decrease on placebo. Both differences were statistically significant, and the 18 percent figure is the one most widely quoted.
The extension phase is the more instructive half, and it is usually omitted from summaries. Participants who continued on tesamorelin for the full 52 weeks broadly held the ground they had gained, showing roughly no further change in one trial and a further small reduction in the other. Participants who had responded during the first 26 weeks and were then switched to placebo regained visceral fat substantially, by 22 percent in one trial and 16 percent in the other.
That pattern defines what the therapy is. It is maintenance rather than cure. The effect persists while treatment continues and reverses when it stops, which is the same shape seen with most metabolic therapies and worth knowing before starting one.
Weight Neutral by Design: Reading the Label Literally
The prescribing information for tesamorelin contains a sentence that is unusual in a field full of weight-loss marketing. It states that the medicine is not indicated for weight loss management, because it has a weight neutral effect.
That is not lawyerly hedging. It is an accurate description of what the trials found. Visceral fat fell measurably while total body weight did not meaningfully change. Fat was redistributed rather than lost in bulk, which is precisely the intended effect in a population whose problem is distribution.
It also means that anyone tracking progress on this therapy with a bathroom scale will conclude, incorrectly, that nothing is happening. The appropriate measures are imaging where available, waist circumference measured carefully and consistently, and the metabolic markers the visceral fat was driving in the first place.
The approved indication is narrow: reduction of excess abdominal fat in adults with HIV-associated lipodystrophy. It is not approved for general abdominal obesity, for cosmetic body contouring, or for anyone without that specific diagnosis. The evidence base sits entirely within that population, and extrapolating an 18 percent visceral fat reduction to people outside it is not supported by the trials.
Monitoring, Trade-offs and the Questions Worth Asking
Stimulating the growth hormone axis has consequences beyond fat tissue, and the label reflects them.
Serum IGF-1 rises during treatment, and the effects of prolonged elevation are described in the label as unknown. That uncertainty is the reason IGF-1 is monitored during therapy. Glucose tolerance can worsen: in the trials, a higher proportion of participants on tesamorelin than on placebo reached an HbA1c of 6.5 percent or above, so glucose and HbA1c warrant monitoring, particularly in a population already at elevated metabolic risk.
Fluid retention is common and can present as peripheral oedema, joint pain or carpal tunnel symptoms. Injection site reactions occur considerably more often than with placebo, and hypersensitivity reactions occurred in a small but meaningful minority. The most frequently reported adverse effects overall were joint pain, injection site redness and itching, limb pain, peripheral oedema and muscle pain.
The contraindications are firm rather than cautionary. The medicine is contraindicated in pregnancy, in people with active malignancy, in people with disruption of the hypothalamic-pituitary axis, and in anyone with known hypersensitivity to it. Because it raises a growth factor, any pre-existing malignancy must be inactive and its treatment complete before therapy begins. Long-term cardiovascular safety has not been established.
None of that makes the therapy unreasonable for the population it was designed for. It does mean the decision requires a clinician who can confirm the diagnosis fits the approved indication, establish baseline measurements worth tracking, review malignancy and glucose risk, and judge whether the measured benefit justifies continuing. That is a genuine clinical assessment rather than a formality, and it is the actual next step for anyone whose situation resembles the one described here.
The broader lesson generalises well beyond this one medicine. When the goal is specific, the measurement should be specific too. A therapy aimed at one fat compartment should be judged by imaging of that compartment and by the metabolic markers it was meant to improve, not by a number on a scale that was never capable of seeing the tissue in question.
Check If the October Batch Is Still Available
99%+ HPLC purity · Third-party tested · Fast U.S. shipping
Due to manufacturing constraints, inventory may be limited.
Frequently asked questions
Is visceral fat testing something to request routinely?
Not usually. Imaging dedicated to visceral fat quantification is mostly a research and trial tool, and few clinical decisions turn on the precise number. For most people, a carefully measured waist circumference tracked over time, alongside blood pressure, fasting glucose or HbA1c, triglycerides and HDL cholesterol, captures the same clinical signal at far lower cost.
Can diet and exercise reduce visceral fat specifically?
Visceral fat does tend to respond earlier and proportionally more than subcutaneous fat to sustained energy deficit and to regular aerobic activity, which is why metabolic markers often improve before much weight is lost. There is no evidence that any particular exercise targets abdominal fat selectively; the effect comes from overall activity and energy balance rather than from working the muscles underneath.
Why does the tesamorelin label say it is not for weight loss?
Because the trials measured no meaningful change in body weight while visceral fat fell. The medicine changes where fat is stored rather than reducing total mass. The label states this explicitly so that it is not prescribed or marketed as a weight-loss treatment, for which it has neither evidence nor approval.
Does the effect last after stopping treatment?
The extension data indicate it does not. Participants switched from tesamorelin to placebo after responding regained visceral fat substantially over the following 26 weeks, while those who continued largely maintained their reduction. The therapy behaves as ongoing treatment rather than a finite course.
Can consumer body composition scales track this?
They can track a trend on one device under consistent conditions, and that is roughly the limit. Bioimpedance readings shift with hydration, recent meals, exercise and skin temperature, and their visceral fat outputs are modelled rather than measured. Comparing a reading between two devices, or treating a single reading as a clinical measurement, is not meaningful.
This is education, not medical advice. Laboratory results only carry meaning alongside your symptoms, history and examination. Talk to a qualified clinician about your own results before changing anything about your care or supplements.


